What Alzheimer’s is, and what we know about why it happens
The difference between dementia and Alzheimer’s, the main types, the stages, what goes wrong in the brain, the competing theories of cause, and who is most at risk.
Last reviewed
16 min read
6 studies cited
Doctors use “dementia” and “Alzheimer’s” as if they were the same thing. They are not. Knowing the difference helps you ask better questions, and it explains why two people with the same label can have very different years ahead of them.
Dementia vs Alzheimer’s
Dementia is an umbrella word. It means memory, thinking or reasoning has declined enough to get in the way of daily life. It describes symptoms. It is not a single disease.
Alzheimer’s disease is one specific brain disease, and the most common cause of dementia. It is defined by two kinds of damage: clumps of a protein called amyloid between nerve cells, and twisted fibres of a protein called tau inside them. It causes an estimated 60–80% of dementia in the United States and 60–70% worldwide.
A comparison that helps many families: “dementia” is like “heart disease”, and “Alzheimer’s” is like a heart attack, one particular cause.
Plate 1.Auguste Deter in 1902. She was the first patient Alois Alzheimer described, in 1906.Public domainPhotographer unknown, 1902. Via Wikimedia Commons.
The main types of dementia
The type matters. It changes what to expect, which medicines are safe, and which treatments are even an option.
Main types of dementiaShares are for dementia cases. Many people have more than one type.
Type
How common
What usually shows first
Worth knowing
Alzheimer’s disease
60–80% of US cases
Short-term memory: repeating questions, forgetting recent talks, getting lost in familiar places
Slow, steady decline
Vascular dementia
5–10% on its own; far more often mixed with Alzheimer’s
Planning, judgment, attention and slowed thinking, often more than memory
Caused by poor blood flow and strokes. Can start suddenly or worsen in steps. Many experts think it is underdiagnosed.
Dementia with Lewy bodiesDLB
About 4% in community studies, 7.5% in clinics
Detailed visual hallucinations, alertness that swings by the hour or day, acting out dreams, stiffness or slowness
Serious reactions to antipsychotic drugs in about half of people. Probably underdiagnosed.
Parkinson’s disease dementia
About 1 in 10 people with Parkinson’s in one UK clinic study
Thinking problems at least a year after Parkinson’s movement symptoms
Same protein as Lewy body dementia. If thinking problems come first or within a year, it is called DLB.
Frontotemporal dementiaFTD
About 50,000–60,000 people in the US
Personality and behavior (loss of empathy, poor judgment) or language. Memory is often fine early.
Usually starts at 45–65. About one-third of cases are inherited.
Mixed dementia
Over half of people diagnosed with Alzheimer’s
A blend of the above
In one autopsy study, 82% had Alzheimer’s changes plus at least one other type.
LATE
Mostly people over 80
Memory loss that looks like Alzheimer’s
Tends to progress more slowly. Often occurs alongside Alzheimer’s. Can only be confirmed after death for now.
LATE stands for limbic-predominant age-related TDP-43 encephalopathy. Figures on how common it is vary widely and we have not yet confirmed them. Other, rarer causes include Down syndrome-associated Alzheimer’s, Huntington’s disease and Creutzfeldt-Jakob disease. Normal-pressure hydrocephalus, which is treatable, is covered on the getting a diagnosis page.
Mild cognitive impairment
Mild cognitive impairment (MCI) means thinking or memory problems that are noticeable and measurable, while the person still manages most daily life on their own. It affects about 12–18% of people aged 60 and over.
It often moves on. An estimated 10–15% of people with MCI develop dementia each year. About 1 in 3 people whose MCI is caused by Alzheimer’s reach dementia within 5 years.
It doesn’t always. MCI can stay stable or go back to normal, especially when the cause is a medicine, depression, poor sleep or another treatable problem.
Two kinds. “Amnestic” MCI mainly affects memory and is more often linked to Alzheimer’s. “Non-amnestic” MCI affects planning, language or visual skills.
The seven stages
Many doctors and hospices use Dr. Barry Reisberg’s seven-stage scale. Its functional version (called FAST) gives typical lengths for each stage. Those times come from Alzheimer’s research in the 1980s, and real people vary a great deal. The scale was built for Alzheimer’s. Lewy body, vascular and frontotemporal dementia often follow a different order.
1
Normal
What you may see
No problems.
2
Very mild decline
What you may see
She notices slips, such as misplaced keys or forgotten names. Others usually don’t. This can be normal aging.
3
Mild decline (about the same as MCI)
Typically about 7 years
What you may see
Family and coworkers start to notice. Complex jobs, travel to new places and complicated planning get hard.
4
Moderate decline (mild dementia)
Typically about 2 years
What you may see
Needs help with bills, money, cooking a full meal, shopping and managing medicines.
5
Moderately severe decline (moderate dementia)
Typically about 1.5 years
What you may see
Needs help choosing the right clothes for the day or the weather. Can no longer live safely alone.
6
Severe decline
Typically about 2.5 years in total
What you may see
Needs help dressing, then bathing, then using the toilet. Loses bladder control, then bowel control. Changes in personality and behavior are common.
7
Very severe decline
Often 1–1.5 years or more for each step within this stage
What you may see
Speech shrinks to a few words, then none. Loses the ability to walk, then to sit up, smile and hold up the head.
Families mostly use the scale for planning. For what to do at each point, see living with Alzheimer’s.
What happens in the brain
Amyloid plaques. A protein fragment called beta-amyloid clumps together between nerve cells. This builds up for years before symptoms appear. (A lead time of 15–20 years is widely quoted but we have not yet confirmed it from a primary source.) Under the 2024 Alzheimer’s Association criteria, an abnormal amyloid test (or a related blood or spinal-fluid p-tau test) is the core sign that defines the disease.
Tau tangles. Inside nerve cells, the tau protein twists into tangles. The 2024 criteria use how far tau has spread to judge how advanced the disease is.
Blood-vessel damage. Small strokes and damaged small vessels often sit alongside Alzheimer’s and add to the harm. That is what “mixed dementia” means.
Inflammation, lost connections between nerve cells, and immune cells called microglia are also widely described as part of the damage. We have not yet confirmed the key studies for these, so we mention them without detail.
Does sleep “wash out” amyloid?
You may have read that the brain cleans itself during sleep. A 2013 mouse study reported faster amyloid clearance during sleep. A 2024 mouse study in Nature Neuroscience found the opposite: clearance was lower during sleep and anesthesia (Miao and colleagues, 2024). Sleep matters for brain health. The “sleep washes out amyloid” story is still argued over and should not be treated as settled.
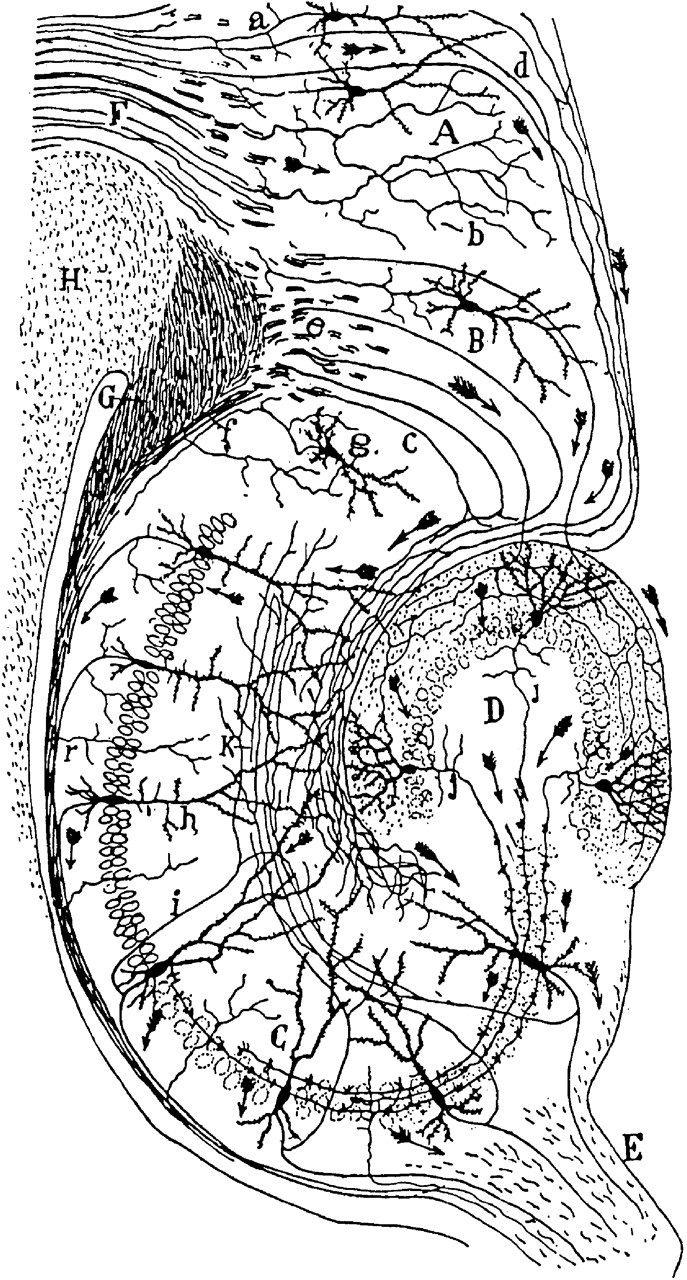
Plate 2.The hippocampus, the brain’s memory hub and one of the first areas Alzheimer’s damages, drawn by Santiago Ramón y Cajal.Public domainSantiago Ramón y Cajal, 1911. Via Wikimedia Commons.
Theories of what causes it
Scientists do not agree on a single cause. Here are the main ideas, what supports each one, and what counts against it. Most researchers now see late-life Alzheimer’s as having several causes that work together.
1. The amyloid theory (the mainstream model)
The idea: amyloid builds up first and sets off tau tangles, inflammation and the death of nerve cells.
For it: People with Down syndrome carry an extra copy of chromosome 21, which holds the amyloid gene (APP). More than 90% of them develop Alzheimer’s in their lifetime. Drugs that clear amyloid slow decline a little. In the lecanemab trial, 1,795 people were followed for 18 months, and decline was 27% slower, a difference of 0.45 points on an 18-point scale. The inherited early-onset genes are often said to all affect amyloid; we have not yet confirmed that from a primary source.
The drug benefit is small, and experts argue over whether patients and families can notice it. See our medicines page.
The side effects are real. In the same trial, brain swelling showed up on scans in 12.6% of people on the drug and 1.7% on placebo. Small brain bleeds showed up in 17.3% and 9.0%.
Many older people are said to have plenty of amyloid and no dementia. This is widely reported, but we have not yet confirmed a reliable figure.
In June 2024 the journal Nature retracted an influential 2006 paper on one form of amyloid (“Aβ*56”) because of manipulated images. That discredited one line of research. It did not overturn the wider amyloid evidence, which rests on genetics and work from many independent labs. The two are often mixed up online. The follow-the-money page has more on funding and research misconduct.
2. The tau theory
Some researchers argue tau, not amyloid, is the main driver of damage, because where tau spreads seems to match symptoms more closely. The 2024 criteria do use tau scans for staging. We have not yet confirmed the key studies behind the stronger claim, so we list it here as an argument, not a finding.
3. The inflammation theory
This theory holds that the brain’s immune cells stay switched on and cause harm, driving the disease rather than just reacting to it. It is an active research area. We have not yet confirmed the key studies, so we give no numbers.
4. The blood-vessel (vascular) theory
Poor blood flow and damage to small vessels may start or speed up the disease. Two facts support it: mixed Alzheimer’s and vascular damage is very common, and high blood pressure, diabetes and high LDL cholesterol are all on the Lancet Commission’s list of risk factors.
5. The metabolic theory (“type 3 diabetes”)
This is the idea that the brain becomes resistant to insulin. The label “type 3 diabetes” comes from a 2008 paper by Suzanne de la Monte and Jack Wands. A 2024 review in Ageing Research Reviews found shared mechanisms and reported that people with diabetes have a 65% higher chance of Alzheimer’s. It concluded the label is defensible but still debated.
So far, treatments built on this idea have not worked. Insulin sprayed into the nose did not help. The semaglutide trials (the same drug family as Ozempic), with 3,808 people, did not slow Alzheimer’s either, although some blood markers improved.
Didn’t work3/5Public / nonprofit
SNIFF: insulin sprayed into the nose for memory loss
Result No benefit for thinking or daily function compared with placebo. This was a direct test of the “type 3 diabetes” idea, and it did not work in this form.
Who paid: National Institute on Aging (reported; not yet confirmed from the paper)
Diabetes is a real risk factor. “Alzheimer’s is just diabetes of the brain” goes further than the evidence.
6. The infection theory
This theory says viruses such as herpes simplex (the cold-sore virus) or other germs trigger amyloid as a defense.
For it: in Wales, people who were just old enough to get the shingles vaccine had 20% fewer new dementia diagnoses over 7 years than people just too old, in a study of 282,541 adults. The effect was stronger in women. Against it: the VALAD trial gave the antiviral valacyclovir to 120 people with early Alzheimer’s and the cold-sore virus for 78 weeks, and found no benefit.
The vaccine finding is strong observational evidence but not proof. Treating the virus after symptoms start has not helped so far.
7. The mitochondria theory
This idea says the decline of the cell’s energy factories (mitochondria) with age comes first. It has less direct evidence in people than the other theories.
Who is at risk
Age
Age is the biggest risk factor by far.
Share of Americans with Alzheimer’s dementia, by ageAlzheimer’s Association, 2026 Facts and Figures.
Age
Share
About 1 in…
65–74
5.2%
19
75–84
13.8%
7
85 and over
35.8%
3
The APOE4 gene
APOE is a gene everyone carries in some form. The ε4 version (APOE4) is the most important common risk gene for Alzheimer’s. Here is the absolute risk, for people aged 65–69, of developing dementia by their early-to-mid 80s.
APOE4 copies and dementia riskAlzheimer’s Association, 2026 Facts and Figures.
Copies of APOE4
Risk by early-to-mid 80s
Out of 100 people
None
5–7%
5 to 7
One
15–16%
15 to 16
Two
31–40%
31 to 40
Two copies (about 2 in 100 people): a 2024 Nature Medicine study argued this is essentially its own genetic form of Alzheimer’s (NIH summary). Almost all had abnormal amyloid by 65. On average, symptoms began around 65, MCI around 72, dementia around 74, and death came around 77. These people make up about 15% of Alzheimer’s cases.
APOE4 is not destiny. Many people with it never develop dementia, and many without it do.
Testing for APOE4 has real consequences for the whole family. Talk to a doctor or genetic counselor before ordering it.
Inherited early-onset Alzheimer’s
Rare changes in three genes (APP, PSEN1 and PSEN2) cause Alzheimer’s that usually starts in a person’s 30s to 50s. These families are often said to make up less than 1% of cases, with each child of a carrier having a 50% chance of inheriting the gene. We have not yet confirmed those figures from a primary source. If Alzheimer’s started very young in several relatives, ask about genetic counseling.
Why women are about two-thirds of cases
Nearly two-thirds of the 7.4 million Americans with Alzheimer’s are women, about 4.5 million people. A 65-year-old woman has about a 1 in 5 lifetime risk.
The main reason is that women live longer, and age is the biggest risk factor.
Researchers are also studying biology, genes and life experience. Ideas include the drop in estrogen at menopause, how APOE4 interacts with sex, and less access to education for earlier generations of women. These specific explanations are not yet confirmed.
Women also give more than 60% of dementia care in the US. Worldwide, the WHO says women give 70% of care hours.
The 14 risk factors people can change
In 2024 the Lancet Commission on dementia listed 14 risk factors people can change (Livingston and colleagues, Lancet 2024). It estimated that about 45% of dementia could in theory be prevented or delayed if all 14 were removed, up from 40% with 12 factors in 2020.
The Lancet Commission’s 14 risk factors (2024)Grouped by the stage of life when each one matters most.
Stage of life
Risk factors
Early life
Less education
Midlife
Hearing loss; high LDL cholesterol (new in 2024, about 7% of dementia); depression; head injury; physical inactivity; diabetes; smoking; high blood pressure; obesity; heavy drinking
Later life
Social isolation; air pollution; untreated vision loss (new in 2024, about 2% of dementia)
We have confirmed the Commission’s share for two factors only (LDL cholesterol and vision loss), so we give no share for the others yet.
“45% preventable” is a population estimate from a model. It does not mean any one person can cut their own risk by 45%. It is not a reason to blame your mother, or yourself, for her diagnosis. For what the trials show about lowering risk, see lowering your risk.
Key numbers
Alzheimer’s in the United StatesAlzheimer’s Association, 2026 Facts and Figures.
Measure
Figure
Americans 65+ with Alzheimer’s dementia
7.4 million
Projected by 2060 without a breakthrough
13.8 million
Official Alzheimer’s deaths, 2024
116,022
Rank as a cause of death
6th overall, 5th at 65+
Rise in Alzheimer’s deaths, 2000–2024
134%
Cost of care for people 65+, 2026
$409 billion
Unpaid family caregivers, 2025
More than 12 million
Hours of unpaid care, 2025
19.6 billion
Value of that unpaid care
$446.3 billion
Death certificates undercount dementia, so the true number of deaths is higher.
Dementia worldwideWorld Health Organization fact sheet, July 2026.
Measure
Figure
People living with dementia (2021)
57 million
New cases each year
Nearly 10 million
Share caused by Alzheimer’s
60–70%
Rank as a cause of death
7th
Global cost (2019)
US$1.3 trillion
How long people live
The Alzheimer’s Association says people live 4–8 years on average after an Alzheimer’s diagnosis, and some live 20 years. The largest review so far, from 2025, shows that age at diagnosis matters more than almost anything else.
Solid4/5Funder not confirmed
How long people live after a dementia diagnosis: the largest review so far
Systematic review and meta-analysis of 261 studies
People
More than 5 million people with dementia
Length
Studies of varying length, pooled
Result Age at diagnosis mattered most. Average life expectancy after diagnosis was 8.9 years for a woman diagnosed at 60 and 2.2 years for a woman diagnosed at 85. For men it was 6.5 years at 60 and about 2 years at 85. People with Alzheimer’s lived up to 1.4 years longer than people with other types. 13% had moved to a nursing home within 1 year, 35% within 3 years and 57% within 5 years. These are averages; any one person can live much longer or shorter.
Who paid: Not yet confirmed.
Conflicts: Not reported
If your mother was diagnosed in her 80s, it is reasonable to plan on a shorter horizon than a family whose mother was diagnosed at 65. The first 30 days page covers the planning that helps in either case.
Words used on this page
Amyloid
A protein fragment (beta-amyloid) that clumps into plaques between nerve cells in Alzheimer’s.
Tau
A protein that normally supports nerve cells. In Alzheimer’s it twists into tangles inside them.
Mild cognitive impairment (MCI)
Measurable memory or thinking problems that do not yet stop a person managing daily life.
APOE
A gene that helps carry fats in the body. Its ε4 version raises Alzheimer’s risk.